1:1 Consultation
PATIENT GUIDE · IBON PLASTIC SURGERY
Dual Canthoplasty: Combining Lateral Canthoplasty and Lower Corner Surgery
A guide to dual canthoplasty at IBON Plastic Surgery in Seomyeon, Busan, where Dr. Ju-Chan Kim combines lateral canthoplasty and lower corner surgery in one operation, covering candidacy, assessment, risks, and recovery.

Dual Canthoplasty: Lateral Canthoplasty and Lower Corner Surgery in One Operation
Medically reviewed by Dr. Ju-Chan Kim, Board-Certified Plastic Surgeon
At IBON Plastic Surgery, dual canthoplasty is the name for two outer-eye procedures performed together under eye corner surgery (canthoplasty): lateral canthoplasty, which extends the outer corner of the eye horizontally, and lower corner surgery, which lowers the outer third of the lower eyelid margin. Both work on the outer part of the eye — one along its length, one along its lower edge. The exact steps depend on the individual plan, because two components drawn into one operation carry more decisions than either alone. This guide sets out what the clinic describes and what that means for a patient.

What the Operation Is
Dual canthoplasty is a simultaneous combination of lateral canthoplasty (outer corner extension) and lower corner surgery (lower-outer eyelid lowering). The aim is to enlarge the outer eye dimension both horizontally and vertically, while reducing the risk of the extended corner re-adhering.
It is worth being precise about what it is not. It does not treat the inner corner. Epicanthoplasty, which addresses the fold at the inner corner, is a separate procedure at IBON (covered in our epicanthoplasty procedure, candidacy, and recovery guide) and is planned on its own terms if it is relevant at all.
Two components, one operation, one plan. The word combination is the whole definition — this is not a stronger version of lateral canthoplasty but a second piece of work along the lower-outer lid, with its own incision, its own healing, and its own ways of falling short.
The Two Components
Lateral canthoplasty extends the horizontal outer eye corner. The lateral canthus is anchored to the periosteum — the tissue covering the bone at the outer orbit — which helps reduce the risk of the corner re-adhering after surgery. On its own, the procedure takes around 30 minutes, with sutures typically removed at 5–7 days.
Lower corner surgery lowers the lateral one-third of the lower eyelid margin by repositioning muscle and skin together. Its purpose is to soften an upward-slanting outer eye while preserving the support of the lower lid.
The two answer different questions. Lateral canthoplasty asks how long the eye can reasonably be at its outer end. Lower corner surgery asks how the lower-outer edge of the eye sits — whether it rises steeply toward the corner or can be eased downward. Combining them changes the outer part of the eye in two directions at once, often alongside double eyelid surgery when a broader eye-shape plan is indicated.
The Published Steps
Three movements, and the second is where the individual plan matters most.
The surgeon plans the outer-corner extension and the lower-lid change together, performs the selected techniques, and closes the treated areas. The exact steps depend on the individual plan.
"The selected techniques" is plural for a reason. How far the corner is extended and how much the lower-outer lid is lowered are chosen for the patient rather than fixed. A published step list detailed enough to cover every combination would be a list of possibilities rather than a description of your operation.
Who Is a Candidate
Suitable candidates are adults with suitable eye anatomy who want change at the outer part of the eye in both directions — a longer outer corner and a softer, lower outer edge of the lower lid — confirmed at a professional consultation.
That wording is worth holding onto when a combined procedure is discussed. Wanting both changes is part of the candidacy, not an upsell. If what bothers you is only the length of the eye, or only an upward slant, that is a reason to ask whether one component would do.
Surgery may need to be postponed, or another approach considered, for patients with uncontrolled medical conditions, active infection around the eyes, or unrealistic expectations. The surgeon assesses each case.
What the Assessment Covers
The surgeon evaluates eye anatomy, the structure of the outer corner and lower lid, skin, and the result the patient hopes for, to determine whether the combined procedure is appropriate.
Two things to notice.
The outer corner and the lower lid are assessed as structures in their own right. How much room there is to extend the corner, and how much support the lower lid has (including whether under-eye fat repositioning or lower eyelid fat repositioning is relevant), are separate findings — and both matter, because lowering a lid that lacks support is a different proposition from lowering one that has it.
And the purpose of the assessment is to decide whether the combination is appropriate — not how much of it. Combining the two is a yes-or-no output of an examination.
What "Enlarging the Outer Eye" Means Here
The clinic describes the combined goal as enlarging the outer eye dimension horizontally and vertically. That phrase is the clearest statement of why the two components are paired.
Lateral canthoplasty on its own changes the eye's length at the outer end. Lower corner surgery on its own changes how the lower-outer lid sits. Together, the outer part of the eye is being reshaped in two directions rather than one — which is why the candidacy language describes wanting both changes, and why the assessment looks at the outer corner and the lower lid separately.
For a patient the useful consequence is about how to describe what you want. "Make my eyes longer" names one direction. Describing the shape you are picturing — longer at the outer end, less sharply upturned, softer along the lower edge — gives the surgeon something to plan against across both components.
It also gives you a way to test a recommendation. If a combined plan is proposed, ask what shape it is aiming at and what each component contributes. A plan that can be described that way has been drawn; one that cannot has been assembled.
Two Components, One Recovery
There is a practical advantage to doing both in one sitting, and it belongs in the decision alongside the cautions.
One operation means one recovery period rather than two, one set of follow-up visits, and — for someone who has traveled — one trip. Both areas settle on overlapping schedules instead of consecutive ones.
Against that, more tissue handled at once generally means more swelling to get through at the same time, and recovery varies according to the techniques used and individual healing.
Neither consideration settles the question. What settles it is whether there is a finding for both components, which is what the assessment is for and what a patient cannot determine alone.
Anesthesia
Eyelid and canthoplasty procedures at IBON are performed under local anesthesia, sometimes with brief sedation, with pain control planned according to the surgery and the patient's needs.
MedlinePlus, the U.S. National Library of Medicine's consumer health service, describes what the options mean: a local anesthetic numbs a limited area while you stay awake, and sedation, where added, comes in graded levels rather than as a single state.
Because two components are performed in one sitting, it is a fair question to ask how long the whole operation is expected to take in your case and what the comfort plan is across it.
What Can Go Wrong
The disclosed risks include swelling, bruising, scarring, infection, asymmetry, and changes in the appearance of the eye corner. Patients are asked to discuss procedure-specific risks with the surgeon.
That last instruction matters, because each component carries considerations of its own. For lateral canthoplasty, the extended corner can re-adhere and shorten again over time; periosteal anchoring is used to help reduce that risk, not to rule it out. For lower corner surgery, the position of the lower lid after it is lowered — including how much of the inner eyelid lining (the conjunctiva) becomes visible, and how well the lid stays supported against the eye — is something to discuss in light of your own anatomy.
So the honest way to read the disclosure is as more than one list: the combined list above, plus what applies to each component in your plan. Ask for both.
Recovery
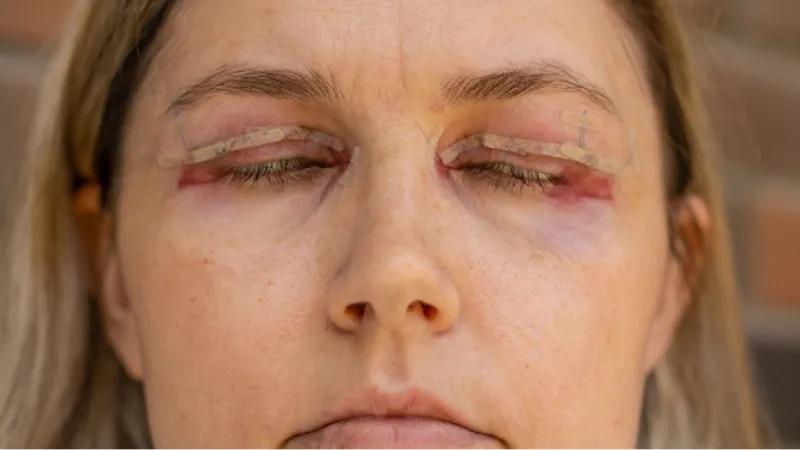
Swelling and bruising are expected after surgery, and recovery varies according to the techniques used and individual healing (similar to the staged progression explained in our double eyelid recovery guide). For incisional eyelid procedures, sutures are typically removed at 5–7 days.
Notice the phrasing — the techniques used, plural again. The overall recovery is not published as a single figure, because it depends on what was done at the corner and along the lower lid.
Duration and visit requirements are likewise matters to confirm at consultation, which makes the schedule a question to ask rather than something to assume when booking travel.
MedlinePlus sets the ordinary expectation for afterwards: discomfort is usual, with swelling and soreness around the treated area to be expected, and the practical move is to ask your own clinician what to expect in your case and when ordinary activity becomes reasonable again.
How Long It Holds
Final results become clearer as swelling settles and healing progresses, with longevity depending on the technique, anatomy, and individual healing.
The same three variables recur. The outer corner and the lower-outer lid can settle on slightly different schedules, which is worth expecting rather than being alarmed by.
Preparation and Aftercare
Preparation follows the surgeon's instructions on medications, medical history, and eye-area care before surgery.
Aftercare means following the prescribed wound-care instructions, protecting the treated area, and attending the follow-up appointments.
"The treated area" is singular in that instruction and plural in practice. The corner and the lower lid are both healing, and both need the same care — which mostly means not rubbing, not straining, and not deciding that one area is fine and can be neglected.
If You Are Traveling For It
Three details shape the trip, and all three are conditional — which is itself the information.
Overall duration needs clinic confirmation. Visit requirements likewise. And recovery varies with the techniques used.
So there is no way to size this trip from published material. The schedule comes from the consultation, and it comes after the plan is drawn, because the plan is what determines it. At minimum, allow for suture removal, which is typically at 5–7 days.
The practical sequence is therefore consultation first, schedule second, flights third. If a return has to be booked earlier for cost reasons, make it changeable and treat the outbound as the only fixed point.
The CDC's guidance for people traveling abroad for medical care adds a complementary point worth carrying: arrange follow-up care before you leave home, and take your own records with you rather than assuming they will follow.
Questions Worth Asking
- Is the finding at both the outer corner and the lower lid, or mainly at one?
- How much extension and how much lowering are you planning, and why?
- What are the specific risks for each component, beyond the combined list?
- How long will the whole operation take, and what is the comfort plan?
- What would change if we did lateral canthoplasty alone and considered the lower lid later?
That last question is the one most worth asking. Candidacy for the combination is described as wanting both changes, so a plan that includes both should be answerable in terms of two findings rather than one preference.
StatPearls describes consent as a discussion covering the nature of the intervention, its balance of risk and benefit, and the alternatives available — here, either component alone, another eyelid procedure, or nothing. MedlinePlus recommends preparing questions beforehand and taking notes during the appointment.
Ask in writing before the appointment — the contact page is the route in, and how the practice describes drawing a plan around one patient sits on the about us page.
One Question Before You Agree
If a combined plan is recommended, there is a single question that tests it, and it is not confrontational.
Ask what would change if only the outer corner were extended.
A surgeon who has drawn a plan can answer it directly — this much of the shape comes from extending the corner, this much from lowering the lower-outer lid, and here is what you would be left with if we stopped at one. A plan assembled rather than drawn tends to answer in generalities.
The way the procedure is described supports asking. Candidacy is written around wanting both changes, and the assessment is described as determining whether the combined procedure is appropriate. Both are yes-or-no formulations, which means the single-component version should already have been considered by the time the combined one is offered.
The Bottom Line
- Dual canthoplasty combines lateral canthoplasty (outer-corner extension) and lower corner surgery (lowering the outer third of the lower eyelid margin) in one operation; it does not involve the inner corner.
- The aim is to enlarge the outer eye horizontally and vertically, with periosteal anchoring of the corner used to help reduce the risk of re-adhesion.
- Candidacy is described as wanting both changes, with suitability determined at consultation.
- The assessment covers eye anatomy, the structure of the outer corner and lower lid, skin, and desired results, to determine whether the combined procedure is appropriate.
- Recovery varies according to the techniques used and individual healing; sutures are typically removed at 5–7 days, and duration and visit requirements are confirmed by the clinic.
Frequently Asked Questions
What is dual canthoplasty?
The combination of lateral canthoplasty, which extends the outer eye corner, and lower corner surgery, which lowers the outer third of the lower eyelid margin, performed in one operation.
Does it change the inner corner?
No. Both components work on the outer part of the eye. Inner-corner surgery (epicanthoplasty) is a separate procedure.
What happens during it?
The surgeon plans the corner extension and the lower-lid change together, performs the selected techniques, and closes the treated areas, with exact steps depending on the individual plan.
Who is it for?
Adults with suitable eye anatomy who want both a longer outer corner and a softer, lower outer edge of the lower lid, after a professional consultation.
How is suitability decided?
By evaluating eye anatomy, the structure of the outer corner and lower lid, skin, and desired results, in order to determine whether the combined procedure is appropriate.
What are the risks?
Swelling, bruising, scarring, infection, asymmetry, and changes in eye-corner appearance, along with considerations specific to each component — such as re-adhesion of the extended corner and changes in lower-lid position — to be discussed with the surgeon.
How long is the recovery?
Recovery varies according to the techniques used and individual healing. Sutures are typically removed at 5–7 days; the overall schedule and visit requirements are confirmed directly with the clinic.
Could I have only one component done?
That is a reasonable question for the consultation. Candidacy for the combination is written around wanting both changes, and the assessment decides whether the combined procedure is appropriate.
This article is for general informational purposes and does not constitute individualized medical advice, and it is not a self-diagnosis tool. Surgical candidacy, technique, and expected outcomes can only be determined through a consultation with a qualified plastic surgeon.
References & Sources
- MedlinePlus — Eyelid Disorders
- MedlinePlus — Anesthesia
- MedlinePlus — After Surgery
- MedlinePlus — Talking With Your Doctor
- CDC Travelers' Health — Medical Tourism
- StatPearls — Informed Consent (NCBI Bookshelf)
- Korean Society of Plastic and Reconstructive Surgeons (KSPRS)
- Archives of Craniofacial Surgery (ACFS)
Every eyelid is different. Bring your questions to a 1:1 consultation with Dr. Ju-Chan Kim for an assessment of your own anatomy.
Book a 1:1 Consultation